Sodium Hypochlorite Accident in Pediatric Dentistry: A Case Report
Saanchi Pediatric Hospital Surat, India, Wisdom Dental Clinics ®, Jaipur, India, Chief Paediatric Dentist at Natkhat Dental Care, Surat, India
ABSTRACT
Sodium hypochlorite (NaOCl) is the most common and effective intracanal medicament used in root canal treatments, because of its very effective antimicrobial activity against microbiota of infected root canals. Sodium hypochlorite is an effective intracanal irrigant and is used in concentrations ranging from 0.5 to 5.25%. At these concentrations, it is highly hypertonic and strongly alkaline with pH 11 to 13. Despite its safe properties, serious complications can result from inadvertent use due to its cytotoxic features. Most of the complications are the result of accidental extrusion of the solution from the apical foramen or accessory canals or perforations into the periapical area. Although it is an effective solution for disinfection of root canal system, fewer incidence of complications are reported, especially in primary teeth. There are few incidence in pediatric patient .Its uncommon in pediatric dentistry but can happen .Present article highlights one of such cases of NaOCl accident and its successful management in a 3 and half year-old child.
KEYWORDS: Complication, Root canal irrigation, Sodium hypochlorite.
INTRODUCTION
Sodium hypochlorite is a commonly used endodontic irrigant. It has the ability to dissolve necrotic and vital pulp tissue. It is a disinfectant against broad-spectrum Gram-positive and Gram-negative bacteria, fungi, spores and viruses; causes biosynthetic alterations in cellular metabolism and phospholipid destruction; forms chloramines that interfere in cellular metabolism; and causes oxidative action with irreversible enzymatic inactivation in bacteria, and lipid and fatty acid degradation. Although it is regarded as safe for endodontic use, the cytotoxic results of accidents must be highlighted; if it comes into contact with vital soft tissue outside the canal system, it can produce serious toxic effects such as haemolysis, ulceration and tissue necrosis of surrounding tissue which leads to secondary infection.1,2
A hypochlorite accident is defined as inadvertent injection beyond the apical foramen. It is a very rare situation but can be life threatening.2,3 Pain is a hallmark of tissue injury during the irrigation, when an accident happens. Swelling of the surrounding mucosa, subcutaneous tissue and skin occurs a few hours later.1,2 Airway compromise should be excluded.1
When confined to the root canal system, these properties enable thorough disinfection. Until now, no other solution has matched the efficacy of NaOCl. However, cytotoxic activity is a well-known shortcoming of NaOCl that may cause acute injuring effects if it reaches the periapical area. In contact with vital tissues, NaOCl quickly oxidizes surrounding tissues leading to rapid hemolysis and ulceration, inhibition of neutrophil migration, and destruction of endothelial and ?broblast cells.4 NaOCl extrusion during root canal therapy (RCT) is commonly referred to as ‘‘the hypochlorite accident’’; it causes acute immediate symptoms and potentially serious sequelae.5
CASE REPORT
A 3 and half year-old boy reported with complain of unilateral swollen face, unable to open left eye after he visited previous clinic. Parents mentioned that previously child complained of pain in upper left side of jaw for this they visited a dentist.
Parents also mentioned that dental treatment started with other dentist 2 days back. While dentist was working on child, parents noticed swelling. Then dentist asked to referred to clinic after 24 hours, but parents were very worried so they rushed to our clinic. Detailed examination revealed Periorbital Edema Swollen Lip bluish discoloration, noticed while lifting a lip tenderness sick look not able to open left eye from parents, previous dentist’s number taken and spoke to a dentist about treatment history.
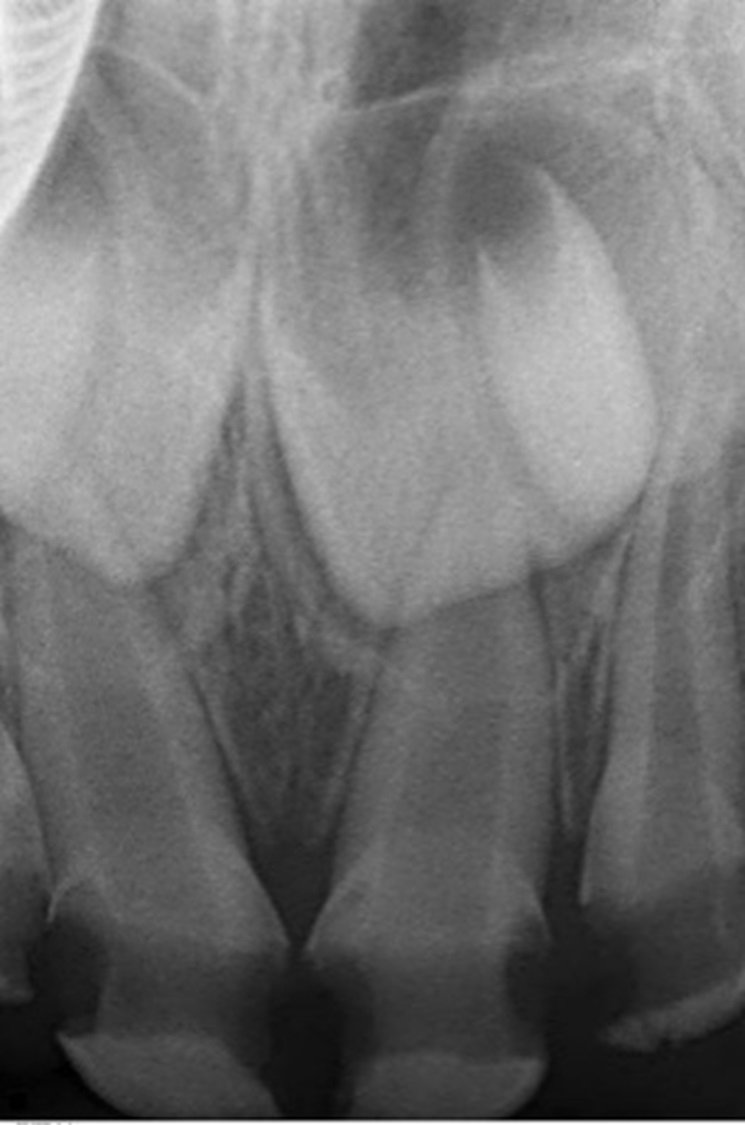
Figure 1:x ray
Previous dentist mentioned that on clinical examination, a deep carious lesion approaching the pulp was seen in upper primary incisor (62). (Figure 1) No periapical pathology was evident. Radiographic interpretation suggested the need of pulpectomy for primary molar. Pulpectomy procedure was initiated after administration of the local anesthesia.
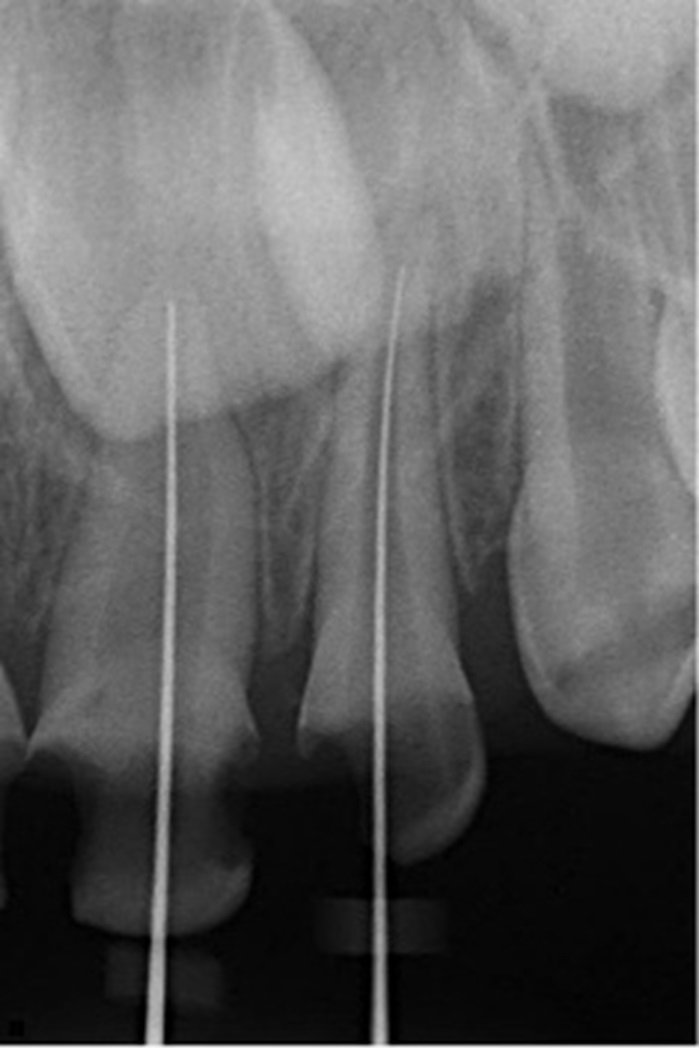
Figure 2: X ray
Access cavity was prepared and the working length was determined. Intermittent canal irrigation with 3% NaOCl was carried out whilst the biomechanical preparation of root canals was on. (Figure 2)
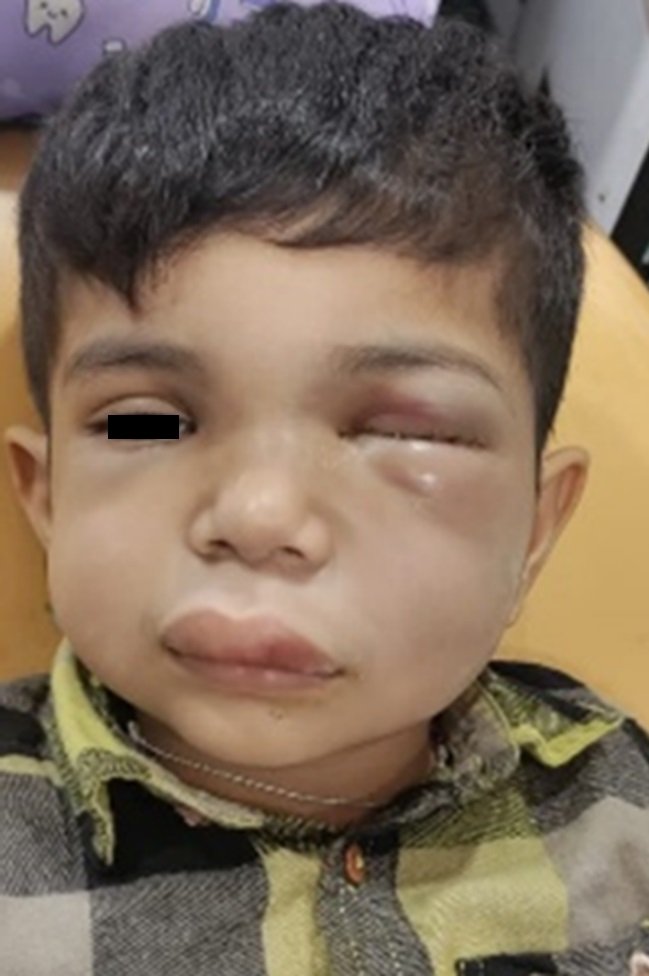
Figure 3: Swelling on face
Patient then was referred to our clinic. It was observed during instrumentation, due to profuse bleeding, copious irrigation with hypochlorite had to be carried out. While irrigating a sudden spontaneous extraoral swelling was observed on the left side of the face which increased gradually extending from the left infraorbital margin to angle of mandible and the patient experienced severe pain. On palpation, the swelling was soft and diffuse. (Figure 3) Crepitus was felt on palpation of periorbital swelling and mouth opening was not at all restricted.
Immediately, NaOCl accident was suspected. The parents were informed about the cause and nature of the incident. Patient and parents were sent to nearby hospital. The patient was immediately referred hospital for further treatment. At the first day of hospitalization, antibiotics, and analgesics were administered intravenously. From the second day of hospitalization, the type of antibiotics. Inj IVF, inj. Arnpoxin, Inj. AVIL, inj. DEXA, inj ENSET, inj Pantac, inj metrogyl, Tab Chymoral forte were prescribed.
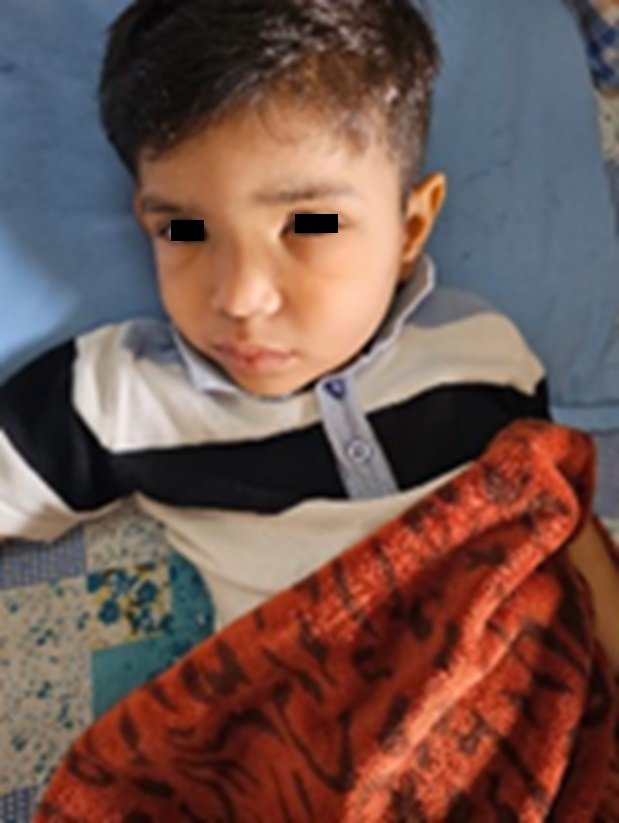
Figure 4: Swelling disappeared
The facial swelling and ecchymosis gradually diminished from the second day; the patient was discharged on the fifth day of hospitalization. Although mild swelling was left on the buccal area, there was no pain on palpation of the affected region and the bluish color of the ecchymosis area faded. (Figure 4)
A week later, the patient revisited our department for follow up. The swelling and ecchymosis had disappeared without other signs or symptoms. The spread in retrograde direction and cause thrombosis of the cavernous sinus. This is specially likely to occur in the presence of infection in upper lip and in the lower part of the nose. This area is therefore called the dangerous area of the face. (Figure 5)
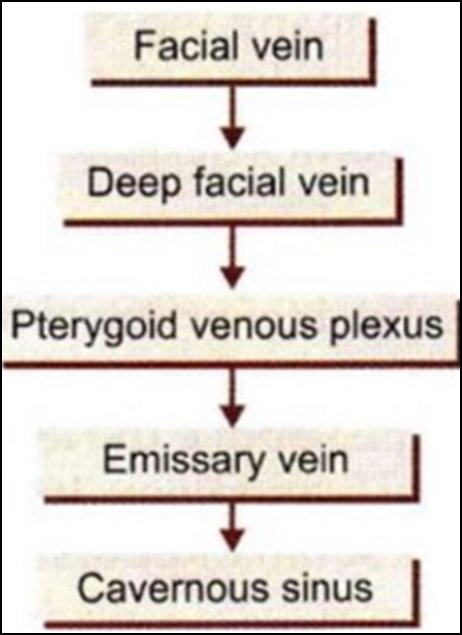
Figure 5: Connection between facial vein and cavernous sinus
DISCUSSION
Due to the cytotoxic nature of NaOCl, occasional complications have been cited in the literature. When it comes into contact with tissue, it causes hemolysis and ulceration, inhibits neutrophil migration, and damages endothelial and fibroblast cells.6,7 Overshooting of the working length, lateral perforation, and wedging of the irrigating needle are the most common etiological factors associated with adverse NaOCl reactions.8 The majority of reported cases of sodium hypochlorite accident occurred as a result of forceful extrusion of NaOCl into the dental root, either by placing the irrigating syringe too far apically or using too high pressure, which pushes the irrigating solution into the periapical tissues.9
According to previous reports, extrusion of NaOCl solution into periradicular tissues during root canal treatment occurs more readily when there is a perforation or wide apex in the treated tooth combined with uncontrolled irrigation force. Sodium hypochlorite causes vascular permeability in blood vessels, probably as a result of damage to the vessels as well as the release of chemical mediators, such as histamine, from involved tissue. This behavior of NaOCl with tissue results into immediate swelling and profuse bleeding through the root canal when NaOCl is not used properly.10 Damage to permanent tooth follicles, peripheral tissue, and oral mucosa have been reported during negligent use of NaOCl use in pediatric endodontics.11
While working sodium hypochloride accident can occur, in such a situation stop treatment immediately and start copious saline irrigation. Regular follow up should be done in such cases.
According to Hülsmann criteria, the diagnostic features of for a NaOCl accident include: (1) acute pain, swelling and redness; (2) bruising; (3) progressive swelling involving the infraorbital area or angle of mouth; (4) profuse hemorrhage often manifesting intraorally from the orifice of the tooth; (5) numbness or weakness of the facial nerve; and (6) secondary infection, sinusitis and cellulitis. In this case, distinguishing features included immediate diffuse infraorbital swelling, profuse hemorrhage and acute pain.Studies on the incidence of NaOCl accident showed that there was higher risk of NaOCl accident in endodontic treatment involving maxillary posterior teeth because of the thin cortical bone cover of the buccal roots.12
If an incident takes place as described in this case occurs, the dentist should remain calm. No specific treatment can reverse the damage from NaOCl. The mainstay of treatment is supportive including control of swelling, pain relief and prevention of secondary infection.13,14,15 Analgesics should be given in order to relieve the post incident pain. A course of antibiotics should be prescribed, as there is potential for secondary or spread of infection. Local anesthesia in the presence of diffuse swelling should be avoided to prevent spreading of existing infection.16 Extraoral cold compresses should be used for the first 6 hours in order to minimize swelling.
Subsequent to this initial period, heat packs should be used after 24 hours (15-minute interval) to improve the circulation to the area. According to Kleir et al, most of the patients recovered completely within one week. The following steps can help clinicians avoid NaOCl accidents:
• Adequate access preparation.
• Good working length control.
• Irrigation needle should be placed 1 to 3 mm short of working length.
• Passive needle tip placement within the canal without getting bound to the walls thus permitting free movements of the needle.
• Irrigant to be expressed into the root canal gently with a low, constant pressure, withdrawing the needle slightly from the binding point.
• Use Luer Lock needles with side-port delivery that are specifically designed for endodontic purposes.17
CONCLUSION
This case report demonstrates that severe complications can occur when sodium hypochlorite is extruded in periapical tissues during endodontic treatment. Although these complications are rare, the dentist should be aware of and have the ability to manage the complications. More caution is needed for teeth with immature apices, root resorption, and apical perforations, to avoid causing extrusion of irrigant from the root canal system into the surrounding tissue during endodontic treatment. If complications occur, the treatment should focus on minimizing swelling, controlling pain, and pre- venting secondary infection. After the treatment of complications, continued observation of the development and eruption of the successional permanent tooth is important.
REFERENCES
- Faras F, Abo-Alhassan F, Sadeq A, et al. Complication of improper management of sodium hypochlorite accident during root canal treatment. J Int Soc Prev Community Dent 2016;6: 493–6.
- Patel E, Gangadin M. Managing sodium hypochlorite accidents: the reality of toxicity. S Afr Dent J 2017;72: 271–4.
- Goswami M, Chhabra N, Kumar G, et al. Sodium hypochlorite dental accidents. Paediatr Int Child Health 2014;34: 66–9.
- Pashley EL, Birdsong NL, Bowman K, et al. Cytotoxic effects of NaOCl on vital tissue. JEndod 1985;11:525–8.
- Farook SA, Shah V, Lenouvel D, et al. Guidelines for management of sodium hypochlorite extrusion injuries. Br Dent J 2014;217 :679–84.
- Gatot A, Arbelle J, Leiberman A, Yanai-Inbar I. Effects of sodium hypochlorite on soft tissues after its inadvertent injection beyond the root apex. J Endod. 1991;17(11):573–574. [PubMed] [Google Scholar]
- Witton R, Henthorn K, Ethunandan M, Harmer S, Brennan PA. Neurological complications following extrusion of sodium hypochlorite solution during root canal treatment. Int Endod J. 2005;38(11):843–848. [PubMed] [Google Scholar]
- Harrison J, Hand R. The effect of dilution and organic matter on the antibacterial property of 5.25% sodium hypochlorite. J Endod. 1980;7:128–132. [PubMed] [Google Scholar]
- Hales JJ, Jackson CR, Everett AP, Moore SH. Treatment protocol for the management of a sodium hypochlorite accident during endodontic therapy. Gen Dent. 2001;49(3):278–281. [PubMed] [Google Scholar]
- Rutberg M, Spangberg E, Spangberg L. Evaluation of enhanced vascular permeability of endodontic medicaments in vivo. J Endod. 1977;3(9):347–351. [PubMed] [Google Scholar]
- Onça O, Hogör M, Hilmio€lu S et al. Comparison of antibacterial and toxic effects of various root canal irrigants. Int Endod J. 2003;36(6):423–432. [PubMed] [Google Scholar]
- Kleier DJ, Averbach RE, Mehdipour O. The sodium hypochlorite accident: experience of diplomates of the American Board of Endodontics. J Endod 2008;34(11):1346-1350.
- Hales JJ, Jackson CR, Everett AP, Moore SH. Treatment protocol for the management of a sodium hypochlorite accident during endodontic therapy. Gen Dent 2001;49(3):278-281
- Farren ST, Sadoff RS, Penna KJ. Sodium hypochlorite chemical burn: case report. NY State Dent J 2008;74(1):61-62.
- Linn JL, Messer HH. Hypochlorite injury to the lip following injection via a labial perforation: case report. Aust Dent J 1993;38(4):280-282.
- Balto H, Al-Nazhan S. Accidental injection of sodium hypochlorite beyond the root apex. Saudi Dent J 2002 Jan-Apr 14(1):36-38.
- Chaugule VB, Panse AM, Gawali PN. Adverse Reaction of Sodium Hypochlorite during Endodontic Treatment of Primary Teeth. Int J Clin Pediatr Dent. 2015 May-Aug;8(2):153-6. doi: 10.5005/jp-journals-10005-1304. Epub 2015 Aug 11. PMID: 26379387; PMCID: PMC4562052.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Parth Shah, Dr. Gaurav Gupta, Dr. Jooie S Joshi. Sodium Hypochlorite Accident in Pediatric Dentistry: A Case Report. Guident. 2024 Nov;17(12). Available from: https://guident.in/articles/pedodontics/sodium-hypochlorite-accident-in-pediatric-dentistry-a-case-report.html