Root Coverage Ability of Connective Tissue Graft
Department of Periodontics, Department of Endodontics, D.J. College Of Dental Sciences and Research Modinagar U.P. India.
INTRODUCTION
Marginal tissue recession is a displacement of the soft tissue margin apical to the cement-enamel junction with exposure of the root surface. The etiology of the gingival recessions is associated with the gingival inflammation, mechanical factors like improper toothbrushing in the circumstances of tooth malposition, bone dehiscence, thin periodontal tissue, and aberrant frenulum(1). The treatment of the gingival recession in the last years includes gingival grafting procedures. The most generally used procedure is the free gingival graft(2). Recentstudies have demonstrated that connective tissue grafting is an effective treatment of gingival recession. The graft used may either be an epithelialized graft or a subepithelial connective tissue graft of palatal masticatory mucosa.
In 1985, Miller[14] established the clinical classification of marginal tissue recessions: class I – the recession does not reach the mucogingival junction without loss of interproximal tissue; class II – the recession reaches or surpasses the mucogingival junction without loss of interproximal tissue; class III – loss of interproximal tissue is seen and the proximal gingival tissue is apically to the enamel-cementum junction and coronally to the recession; class IV – proximal gingival tissue is at the recession base level. The higher the periodontal tissue loss (Miller’s class III and IV), the worse the prognosis related to root coverage amount obtained after surgery.
The aim of this study is to describe a case report using subepithelial conjunctive tissue graft, as well as to show the technique’s success predictability when well indicated.
CASE REPORT
22 years-old, female patient , systemically health, non-smoking, presented as chief complaints the esthetic deficiency at tooth #14 (figure 1) and dentinal hypersenstivity in this same tooth.
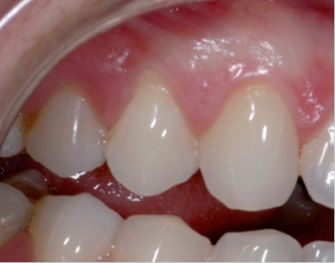
Fig 1 : Initial appearance
After initial diagnosis , the probable etiological factors were defined as traumatic toothbrushing and orthodontic movement. Clinically, the tooth presented a marginal tissue recession of about 2 mm length, with lack of probing depth greater than 2 mm (figure 2). Therefore, the recession was classified as Miller’s class I and, then, root coverage by subepithelial conjunctive tissue graft was indicated.
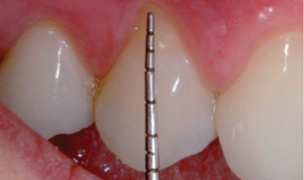
Fig 2 : 2-mm length recession
Antisepsis was carried out through aqueous solution of 0.12% chlorhexidine digluconate. After local anesthesia with 2% mepivacaine with adrenalin, scaling and root planing were executed on tooth #14 (figure 3). Scaling procedure is necessary to remove the contaminated and exposed cementum.

Fig-3 Scalling and root planinig
Then, preparation of the receptor site was performed through horizontal incisions, towards enamel-cementum junction direction, at each papilla (figure 4). Following, two vertical relaxing incisions and one intrasulcular incision were executed (figure 5). Next, full-thickness flap was raised, up to the mucogingival junction and continued as a partial-thickness flap based on this junction. Later, the papilla’s epithelium was coronally removed up to their apexes.
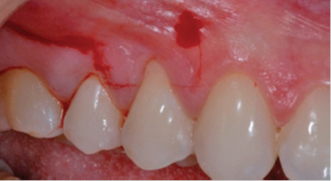
Fig 4 : Horizontal and vertical relaxing incisions
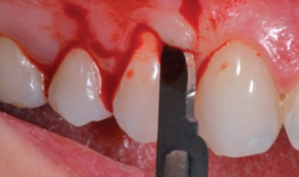
Fig 5 : Intrasulcular incision
After preparing the receptor site, we obtained the subepithelial conjunctive tissue graft from the palate, through the technique of two parallel incisions: one perpendicular to the tooth axis and the other parallel to the bone surface, deepening up to the desired graft height (figure 6).

Fig 6 : Parallel incisions performed on the palate (donator site)
The graft was adapted onto the donator site (figure 7) through sutures with absorbable thread.

Fig 7 : Graft adaptation through absorbable sutures
A suspensory suture was performed (silk thread 4-0), aiming to position the flap coronally onto the graft (figure 8) to improve therefore the graft’s stabilization and nutrition on the receptor site. Also, complementary sutures were executed.

Fig 8 : Final suture positioning the flap coronally.
The donator site was also sutured with 4-0 silk thread (figure 9).
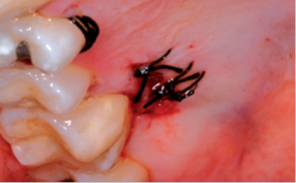
Fig 9 : Donator site sutured
At postoperative period, patient was oriented to use aqueous 0.12% chlorhexidine digluconate mouthrinse for 10 days, and analgesics for pain. Sutures were removed 7 days post-surgery. At 15, 30, and 60 days, as well as 6 months and 1 year, patient’s follow-up was performed, in which were seen a good root coverage and significant aesthetic improvement(figures 10, 11, 12, 13, and 14).
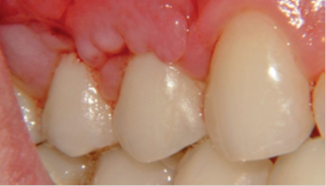
Fig 10 : Postoperative period (15 days)
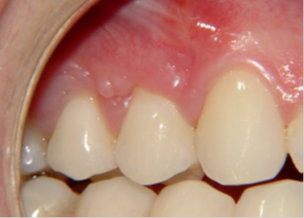
Fig 11 : Postoperative period (30 days)
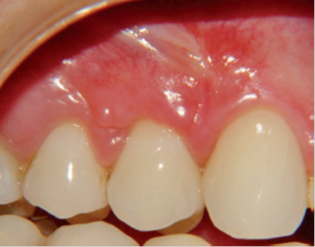
Fig 12 : Postoperative period (60 days)

Fig 13 : Postoperative period (6 months)

Fig 14 : Postoperative period (1 year)
DISCUSSION
Several mucogingival techniques have been introduced in literature aiming to correct marginal tissue recessions[19]. During the decades of 1960s and 70s, the most used techniques were coronally positioned flap[1], laterally displaced flap[9], and the combination of coronally positioned flap with free gingival graft[2]. At the beginning of the decade of 1980s, the use of subepithelial conjunctive tissue graft was disseminated, assuring the obtainment of excellent results in areas with localized root exposure[13].
The choice of the adequate technique and the long-term success of the procedure depend on the careful evaluation of the defect type, recession’s etiology, operator’s ability, presence of keratinized tissue, tissue width, predictability, single or multiple gingival recessions, healing, aesthetic result, and risk factors[15].
Subepithelial connective tissue graft can be indicated for the treatment of single or multiple gingival recessions, correction of the papilla’s volume or deformities of the edentulous gingival border, creation and/or increasing of the amount of the keratinized mucosa [1], and perspective improvement of the root coverage associated with restorative procedures, abrasion, or dental caries[17].
In 1985, Langer and Langer[13] described a technique of subepithelial conjunctive tissue graft for root coverage in the treatment of recessions at single or multiple areas, attributing the procedure success to the double blood supply for the graft’s nutrition, originating from the connective tissue of both the periosteum and flap. Additionally, this aforementioned technique is less invasive at the palatal area, causing a minimum postoperative discomfort to patient and offering a great predictability of coverage. Consequently, this technique is the first choice in cases needing good aesthetical outcomes, as the case reported here. Notwithstanding, this methodology also exhibit disadvantages: need of a greater amount of tissue than the required for covering the area due to the contraction suffered by the tissue, from the surgery to its functional incorporation within the receptor site[7]; and difficulty of standardization of the graft thickness, which may result in aesthetical alterations[3]. Accordingly, these aspects must be observed during the surgical procedure.
CONCLUSION
In the limitations of this case the connective tissue graft procedure led to tissue root coverage, shallow residual probing depths, gain in clinical attachment and an increase in gingival height and width, which is a premise for better maintenance of the achieved root coverage. The epithelial acollar approach led to better gain of attached gingival. Special attention should be given concerning to subepithelial conjunctive tissue graft indication in cases of Miller’s class III and IV marginal tissue recession. The aforementioned technique presents less predictability of root coverage in such recessions, because of the difficulty of graft’s adaptation and nutrition which may result in necrosis[16].
REFERENCES
- Bernimoulin JP, Luscher B, Muhlemann HR. Coronally repositioned periodontal flap. Clinical evaluation after one year. J Clin Periodontol. 1975;2(1):1-13.
- Caffesse RG, Guinard EA. Treatment of localized gingival recessions. Part II. Coronally repositioned flap with a free gingival graft. J Periodontol. 1978;49(7):357-61.
- Callan DP, Silverstein LH. Use of acellular dermal matrix for increasing keratinized tissue around teeth and implants. Pract Periodontics Aesthet Dent. 1998;10(6):731-4.
- Cardoso RJA, Gonçalves EA. In: Proceedings of the 20th Congresso Internacional de Odontologia; 2002. São Paulo: Artes Médicas; 2002. p. 201-48.
- Duarte AC. Cirurgia periodontal pré-protética e estética. São Paulo: Santos; 2002. p. 3-19.
- Edel A. Clinical evaluation of free connective tissue grafts used to increase the width of keratinised gingiva. J Clin Periodontol. 1974;1(4):185-96.
- Edel A. The use of a free connective tissue graft to increase the width of attached gingiva. Oral Surg Oral Med Oral Pathol. 1975;39(3):341-6.
- Fontanari LA, Rodrigues MR, Scremin EI, Kitano MSI, Sampaio JEC, Trevisan Júnior W. Enxerto de tecido conjuntivo subepitelial: uma alternativa em cirurgia plástica periodontal. Perionews. 2009;3(2):131-5.
- Guinard EA, Caffesse RG. Treatment of localized gingival recessions. Part I. Lateral sliding flap. J Periodontol. 1978;49(7):351-6.
- Harris RJ. The connective tissue and partial thickness double pedicle graft: a predictable method of obtaining root coverage. J Periodontol. 1992;63(5):477-86.
- Holbrook T, Ochsenbein C. Complete coverage of the denuded root surface with a one-stage gingival graft. Int J Periodontics Restorative Dent. 1983;3(3):8-27.
- Hokett SD, Peacock ME, Burns WT, Swiec GD, Cuenin MF. External root resorption following partial-thickness connective tissue graft placement: a case report. J Periodontol. 2002;73(3):334-9.
- Langer B, Langer L. Subepithelial connective tissue graft technique for root coverage. J Periodontol. 1985;56(12):715-20.
- Miller Jr. PD. A classification of marginal tissue recession. Int J Periodontics Restorative Dent. 1985;5(2):8-13.
- Ottoni J, Magalhães LF. Cirurgia plástica periodontal e periimplantar: beleza com proporção e harmonia. São Paulo: Artes Médicas; 2006. 440 p.
- Polson AM. Periodontal regeneration: current status and direction. Hong Kong: Quintessence Books; 1994. p. 53-70.
- Nevins M, Melloning JT. Periodontal therapy: clinical approaches and evidence of success. Tokyo: Quintessence; 1998. p. 355-64.
- Steffens JP, Santos FA, Pilatti GL. Cirurgias mucogengivais para recobrimento radicular: o enxerto de conjuntivo subepitelial como técnica de sucesso para defeitos isolados. Dental Science. 2008;2(7):207-14.
- Wennstrom JL. Mucogingival therapy. Ann Periodontol. 1996;1(1):671-701.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Shubhendu Saraswat, Dr. Disha Saraswat. Root Coverage Ability of Connective Tissue Graft. Guident. 2013 Aug;6(10). Available from: https://guident.in/articles/pedodontics/root-coverage-ability-of-connective-tissue-graft.html