Treatment of an Immature Tooth with a Necrotic Pulp Using Platelet-Rich Fibrin
K.D Dental College, Mathura, India
ABSTRACT
AIM:To discuss the clinical and radiological outcome of a procedure in an immature tooth with a necrotic pulp using platelet-rich fibrin (PRF), a second-generation platelet concentrates.
SUMMARY: A 15-year-old female reported with pain in the maxillary anterior region as a result of the injury to her immature right maxillary central incisor tooth. After preparation of the access cavity, the necrotic pulp was removed and the canal irrigated using 0.9% normal saline solution. The canal was then dried and packed with triple antibiotic paste for 3 weeks. After removal of the antibiotic paste, a 5 mL sample of whole venous blood was drawn from the patient's forearm to prepare PRF. The freshly prepared PRF was condensed in the canal until the cement-enamel junction. Three millimetres of white MTA was placed directly over the PRF clot. Three days later, the tooth was restored using a permanent restoration. At 6 month recall, the tooth was asymptomatic with no sensitivity to percussion or palpation. Radiographic examination demonstrated slight thickening of root canal walls, root lengthening and apical closure.
KEYWORDS: Growth factors; immature tooth; open apex; platelet-rich fibrin.
INTRODUCTION
Regenerative endodontic procedures are biologically based procedures which deals with the regeneration of pulp like tissue, more idealistically the pulp-dentin complex, damaged coronal dentin such as that following a carious exposure or trauma; and regenerate resorbed root, cervical or apical dentin.1The mechanics behind the revitalization endodontic procedure is that, despite the tooth being necrotic, some pulp tissue can survive apically which under favorable conditions proliferate to aid in the process of regeneration.2 Although there are no established standardized treatment protocols for endodontic regeneration, many of these cases have shown favorable results, with continued radiographic evidence of development of the dentin-pulp complex and an absence of clinical symptoms.2
The conventional method of revitalization procedure was done by inducing bleeding into the pulp canal by mechanically irritating the periapical tissues. In necrotic teeth with open apices, some amount of pulp tissue along with Hertwigs Epithelial Root Sheath may survive apically and these tissues can proliferate once the inflammatory condition are reversed and the canal becomes totally disinfected.2 The created blood clot acts as a matrix for the in-growth of new tissues into the pulp canal. However, this procedure will cause discomfort for the patient while mechanically irritating the periapical tissues.
In the past two decades, an increased understanding of the physiological roles of platelets in wound healing and after tissue injury has led to the idea of using platelets as therapeutic tools. Platelet-Rich Plasma (PRP) consists of a limited volume of plasma enriched with platelets, which is obtained from the patient. The use of PRP as a potentially ideal scaffold for regenerative endodontic therapy has been documented in the literature.3 However, the use of bovine thrombin for the activation of Platelet Rich Plasma (PRP) has been an issue of controversy which led to the development of the second generation Platelet concentrate known as Choukroun's Platelet Rich Fibrin (PRF) which is totally autologous in nature.4,5 PRF was developed in France by Choukrounet al, in 2001.4 This technique is very simple and inexpensive. PRF contains platelets, growth factors, and cytokines that might enhance the healing potential of both soft and hard tissues.5 Literature survey reveals that there is an absence of documentation regarding the application of PRF in the field of regenerative endodontics.
CASE REPORT
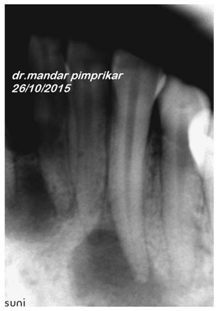
A 15 year old female came with the chief complaint of broken upper front tooth. Past dental history revealed trauma to her upper front tooth. The patient was asthmatic. Intraoral examination of her teeth revealed Ellis class III fracture. Tooth was sensitive to both percussion and periapical palpation tests. It did not respond to CO2 ice and electric pulp test (EPT). Periodontal probing depth of the tooth was within normal limit. Intraoral Periapical Radiographic examination of tooth revealed an immature root and an open apex associated with periapical radiolucency (fig.1).
Further radiographic examination of the tooth revealed open apex along with thin dentinal walls that appeared prone to fracture. So a clinical decision of performing a endodontic treatment using Choukroun's Platelet Rich Fibrin was decided. A written informed consent was obtained from the patient's mother. Local anesthesia was achieved using Lignocaine (1:100000 adrenaline, DJ Lab, India). Access cavity preparation was done on the tooth. The canal was thoroughly irrigated with 20 ml of 0.9% normal saline solution. Following this, irrigation was done using 10ml of hexidine solution (0.2% Chlorhexidine, Vishal Dentocare, India) and dried with paper points (DentsplyMailleferBallaigues). A mixture of Ciprofloxacin (Cifran 500mg, Ranbaxy Lab, India), Metronidazole (Metrogyl 400mg, J.B.Chemicals and Pharmaceuticals, India), and Minocycline paste (Minoz 50 mg, Ranbaxy Lab, India) was prepared into a creamy consistency and introduced into the canal using a lentulospiral. A cotton pellet was placed and the cavity was temporarily sealed with cavit (Dental Products of India, India).
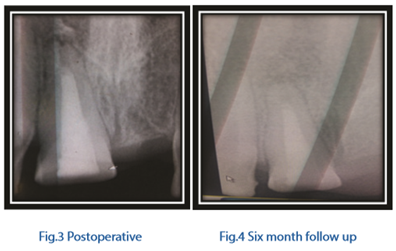
The patient returned after 21 days to the clinic and was asymptomatic. The access cavity was reopened and thoroughly irrigated with sterile saline solution and dried with paper points. A 5 ml sample of whole blood was drawn intravenously from the patient's right antecubital vein and centrifuged (REMI Model R-8c with 12×15ml swing out head) under 3000 rpm for 10 minutes to obtain the PRF which was jelly like in consistency (fig.2). The PRF was condensed into the canal using a finger plugger (DentsplyMailleferBallaigues) till the level the cementoenamel junction. White MTA (ProRoot MTA; Dentsply) was placed directly over the PRF to a thickness of 3mm followed by a wet cotton pellet and cavit. The patient was recalled after 24hrs and the setting of MTA was confirmed. The access cavity was then double sealed with GIC and Composite restoration (fig.3).
The patient returned to the clinic after 6 months for review and was asymptomatic; the tooth showed negative response to percussion and palpation tests. Radiograph revealed continued thickening of the dentinal walls, root lengthening, regression of the periapical lesion and apical closure (fig.4). The patient is still under review.

Fig.1 Preoperative
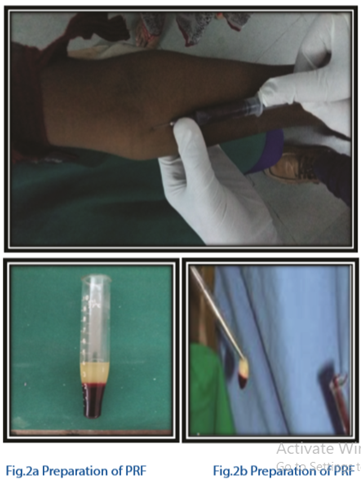
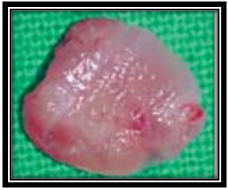
Fig.2c Preparation of PRF
DISCUSSION
This case underscores the potential of necrotic, infected root canal spaces to gain some form of vital tissue. Banchs and Trope documented a case report where revascularization of immature permanent teeth with apical periodontitis was made possible by inducing blood clot into the pulp canal by mechanically irritating the periapical tissues which they attributed to the total disinfection of the canal.2However, this procedure might cause discomfort for the patient. So there was a quest for a better approach in regenerative endodontics which led to the introduction of Platelet Rich Plasma in the revitalization procedures.3
PRP can either be activated by bovine thrombin or calcium sulfate. However, there is an ongoing debate regarding the bovine thrombin which is used in the activation of PRP. Bovine thrombin has been reported to cause adverse reactions like hemorrhage, thrombosis and substantial immune reactions like Systemic Lupus Erythematosus (SLE). Calcium sulfate is also used in the activation of PRP with equal efficacy as that of bovine thrombin with no adverse effects.6 Nevertheless, the process of preparation of PRP is time consuming and difficult compared to PRF.
PRF has been shown to have several advantages over traditionally prepared platelet-rich plasma. Its chief advantages include ease of preparation and lack of biochemical handling of blood, which makes this preparation strictly autologous.4,5 Recently, studies have demonstrated that the PRF has a very significant slow sustained release of many key growth factors like PDGF and TGF β for at least 1 week and up to 28 days, which means that PRF could release growth factors with its own biological scaffold for wound healing process. This leads to the idea of using PRF as a capping agent for reparative dentin formation or as a biomaterial for pulp regeneration. Unlike the PRP, PRF by Choukroun's technique does not dissolve quickly after application; instead the strong fibrin matrix is slowly remodeled in a similar way to a natural blood clot.4,5
Triple antibiotic paste was used for disinfection of the canal because this particular combination is effective in addressing the diverse flora present in the root canal. Sato et al, investigated this drug combination in vitro and found it to be very effective in the sterilization of carious lesions, necrotic pulps, infected root dentin and periapical lesions.7This drug combination is also effective in killing the bacteria in the deep layers of root canal dentin.
Directly over the PRF clot the MTA was packed and condensed to obtain a tight coronal seal as it is hydrophilic and needs moisture to set, which is a favorable property when there is potential for moisture contamination in the clinical setting, and also MTA by itself provides signaling molecules for the growth of the stem cells.8 The positive response to cold test and EPT testing in our case report can be attributed to the placement of MTA slightly below the level of CEJ. If we had got negative response to the vitality testing it could have been due to the thickness of MTA which halts the growth of the new tissue ahead of it and also if placement of MTA is near CEJ the chances of eliciting a positive response is high.3 Based on research in avulsed teeth and on a recent study on infected teeth, it is more likely that the tissue in the pulp space is more similar to periodontal ligament than to pulp tissue. It appears that there is about a 30% chance of pulp tissue re-entering the pulp space.8
Kling suggested that an apical opening greater than 1mm mesiodistally was associated with successful revascularizationof avulsed permanent teeth, while no revascularizationoccurred in teeth with a smaller apical opening.9On the basis of the results obtained in our case report we conclude that revitalization of necrotic infected immature tooth is possible under conditions of total canal disinfection and PRF is an ideal biomaterial for pulp-dentin complex regeneration. The only disadvantage we faced with PRF was its manipulation to place inside the canal. Clinical trials are necessary to compare the effect of PRP, PRF and Induced bleeding in the revitalization of tooth with necrotic pulp and open apex on a long term basis.
REFERENCES
- Murray PE, Garcia-Godoy F, Hargreaves KM. Regenerative endodontics: A review of current status and a call for action. J Endod2007; 33:377–90.
- Banchs F, Trope M. Revascularization of immature permanent teeth with apical periodontitis: New treatment protocol? J Endod2004; 30:196–200.
- Torabinejad M, Turman M. Revitalization of tooth with necrotic pulp and open apex by using platelet-rich plasma: A case report. J Endod2011;37:265–8.
- Dohan DM, Choukroun J, Diss A, Dohan SL, Dohan AJ, Mouhyi J, et al. Platelet-rich fibrin (PRF): A second-generation platelet concentrate. Part I: Technological concepts and evolution. Oral Surg Oral Med Oral Pathol Oral RadiolEndod.2006;101:e37–44.
- Huang FM, Yang SF, Zhao JH, Chang YC. Platelet-rich fibrin increases proliferation and differentiation of human dental pulp cells. J Endod.2010;36:1628–32.
- Intini G, Andreana S, Intini FE, Buhite RJ, Bobek LA. Calcium sulfate and platelet-rich plasma make a novel osteo inductive biomaterial for bone regeneration. J Transl Med. 2007;5:13
- Windley W, 3rd, Teixeira F, Levin L, Sigurdsson A, Trope M. Disinfection of immature teeth with a triple antibiotic paste. J Endod.2005;31:439–43.
- Wang X, Thibodeau B, Trope M, Trope M, Lin LM, Huang GT. Histologic characterization of regenerated tissues in canal space after the revitalization/revascularization procedure of immature dog teeth with apical periodontitis. J Endod.2010;36:56–63
- Kling M, Cvek M, Mejare I. Rate and predictability of pulp revascularization in therapeutically reimplanted permanentincisors. Endod Dent Traumatol 1986;2:83-9.
Disclaimer from Guident
The views and opinions expressed in articles published in Guident are solely those of the authors and do not necessarily reflect the views of the editors, the editorial board or the publisher, Ivory India. Guident does not endorse any product, technique or treatment described. Clinical content is intended for qualified dental and medical professionals and is not a substitute for individual clinical judgement. Guident, its editors and the publisher accept no liability for any consequence arising from the use of information published in the journal.
How to cite this article
Dr. Sonal Bansal Dr. Rohit Paul Dr. Ajay Nagpal Department of Conservative Dentistry and Endodontics. Treatment of an Immature Tooth with a Necrotic Pulp Using Platelet-Rich Fibrin. Guident. 2017 Nov;10(12). Available from: https://guident.in/articles/endodontics/treatment-of-an-immature-tooth-with-a-necrotic-pulp-using-platelet-rich-fibrin.html